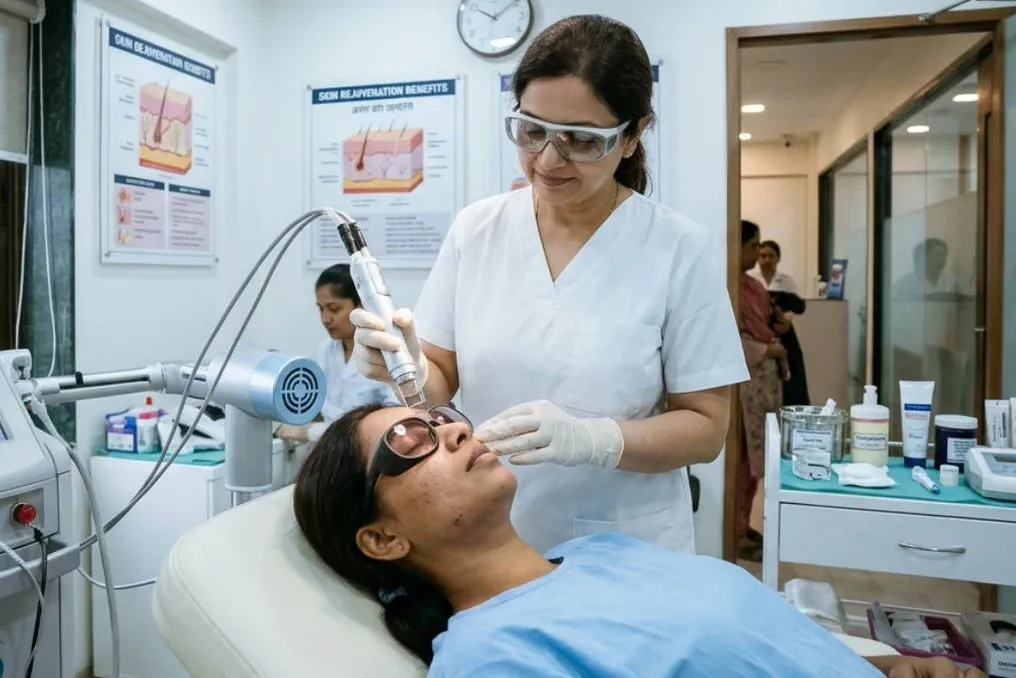
In India's visually content-driven social media culture, a boom in cosmetic clinics has occurred, fueled by the 'Glow Up' algorithm on Instagram. This trend, showcasing dramatic transformations and promises of '100% guaranteed acne elimination,' has turned cosmetic medicine into part of mass culture, making procedures resemble buying fashionable shoes—instant gratification with a single click.
However, behind the glossy facade lies a market situation reminiscent of the Wild West, where non-clinical salons, specialists with short certifications, and non-medical personnel offer a wide range of services, from laser hair removal to fillers. While videos create an impression of accessibility and low cost for procedures, this information noise confuses potential clients and increases the risk of unsuccessful interventions.
To halt this commercial frenzy and protect patients from predatory marketing, the National Medical Commission (NMC), the apex regulator of medical practice in India, has introduced strict ethical norms. The goal of these measures is to clearly delineate between legitimate clinical care and commercial hype.
Differences between dermatology and cosmetology
The main source of misunderstanding among consumers is the mistaken belief that a dermatologist and a cosmetologist are the same. In reality, they differ, and confusing these concepts can lead to serious skin damage.
A dermatologist undergoes extensive eight-and-a-half-year medical training, which includes obtaining a Bachelor of Medicine and Bachelor of Surgery (MBBS) degree, followed by a three-year specialization (MD or DNB) in dermatology, venereology, and leprosy. This program also covers extensive practical training in clinical pathology, complex skin diseases, dermatologic surgery, and laser medicine. Similarly, a plastic surgeon undergoes specialized postgraduate surgical training (MCh or DNB) in reconstructive and aesthetic surgery.
On the other hand, 'cosmetology' is not recognized as a medical specialty or postgraduate qualification within the NMC system. In practice, this term is often used to describe salon aestheticians, technicians, or operators who are not involved in core medical practice and hold short-term diplomas from private, unaccredited institutions.
According to NMC regulations, non-clinical specialists, operators not related to clinical practice, and salon technicians are strictly prohibited from performing procedures such as laser rejuvenation, deep chemical peels, hair transplantation, or injectable dermal fillers. Dr. Tanvi Gupta Arora, a dermatology consultant at CK Birla Hospital, notes: 'Previously, the term 'cosmetology' did not exist in medical residency. Aesthetic procedures were an integrated part of our clinical program under Dermatologic Surgery, including practical surgical training under senior mentors.'
She adds that 'the problem in India was that regulation was historically weak. Non-clinical entities, such as salon technicians and holders of short-term diplomas, began performing deep chemical peels, aggressive laser treatments, and recommending fillers without clinical supervision.'
NMC Rules: What will change in your feed
If your favorite clinic's page on social media suddenly becomes quieter, it is due to NMC rules. Doctors can no longer post 'before and after' promotional photos, reels, or retouched results on public pages. Clinical photographs are permitted exclusively for anonymized, scientific, or educational use. These rules establish clear boundaries for service advertising, social media usage, and influencer engagement.
There is also a ban on bartering with influencers: free Botox, fillers, or hair transplants provided in exchange for 'spontaneous' positive reviews are now completely prohibited. Doctors are not allowed to request or use patient video testimonials or star rating screenshots.
Furthermore, exaggerations and guarantees are forbidden. Phrases like 'Best dermatologist in Delhi,' 'No. 1 plastic surgeon,' or '100% smooth skin guarantee' are illegal. Doctors also cannot claim non-existent qualifications (such as 'Certified Plastic Surgeon according to US standards,' which do not exist in India).
The use of synthetic patient cases, face filters, or AI-generated synthetic doctor voices without a clear disclaimer is prohibited. Moreover, clinics cannot pay marketing agencies commissions 'per patient.'
Dr. Vivek Gupta, a consultant in plastic and cosmetic surgery at Madhukar Rainbow Children’s Hospital, Delhi, states: 'In a field where social media creates unrealistic expectations, solutions must be based on clinical viability, not advertising claims. Restrictions on promotional photos and reviews mean we have to adapt our communication strategies.'
He also mentioned the update to advertising guidelines at his own clinic: 'Our clinic now focuses on public education led by experts, rather than promoting individual results.'
Shifting Strategy: Before and After Implementing Guidelines
Daily operational changes in Indian aesthetic clinics are quite noticeable. In the former, largely unregulated aesthetic medicine market, clinics relied on visual content demonstrating dramatic transformations, which could give the impression that such results were achievable for everyone.
With adherence to NMC norms, clinics are shifting towards educational content, such as anatomical diagrams, procedure explanations, and videos about skin science. Instead of promoting individual treatment outcomes, these formats help clarify medical conditions, the principle of how procedures work, and what patients need to know before deciding on treatment.
Dr. Vivek Gupta acknowledges that while digital platforms remain an important source of information for people researching aesthetic options, restricting promotional material creates certain communication difficulties. He notes: 'Restrictions on reviews, promotional photos, and advertising can make it difficult to inform about treatment results and recovery experience.'
Nevertheless, he insists that 'the solution lies in adapting communication strategies, not compromising ethical standards. Clearer guidelines on distinguishing medical education from commercial promotion would help professionals remain informative while adhering to professional norms.'
He explains that his practice uses digital platforms to discuss common cosmetic issues, treatment options, recovery expectations, and potential risks, such as acne scars or skin aging, while strictly avoiding exaggerated claims or guaranteed results. 'The goal is to build trust through scientifically accurate information and responsible communication, not through promotional testimonials.'
This strategic review also extends to how doctors interact with the public on digital platforms. Dr. Tanvi Gupta Arora points out that sponsored endorsements and pop-up phone numbers over educational reels are now strictly forbidden. 'According to the guidelines, we cannot make sponsored product endorsements or display clinic phone numbers over educational videos,' she emphasizes. 'If I post an educational reel about acne, I disable comments to prevent direct prescribing in social media. We redirect inquiries through proper clinical consultations or telemedicine.'
In her experience, this levels the playing field for doctors who built their practice on 'clinical work, not huge advertising budgets.'
Education vs. Stealth Marketing
In an era where skincare trends go viral overnight in reels and shorts, the line between public health awareness and disguised product placement is dangerously blurring. Stricter control by the NMC is directly aimed at this hidden market, banning barter deals where influencers exchange mentions for free treatment.
Dr. Vivek Gupta stresses that the true test of educational content lies in its intent and presentation. 'The difference is in the purpose and presentation of the information. Public health education helps people understand cosmetic problems, treatment options, preventive measures, and potential risks,' he explains. 'Stealth marketing uses educational content to promote a specific procedure or commercial interest. Every message must prioritize scientific accuracy, balanced information, and patient well-being, not the encouragement of purchasing a specific service or product.'
When asked about working with non-medical influencers, Dr. Gupta stated that he never relied on them for endorsements. 'Aesthetic procedures require individual assessment, and their suitability, risks, and outcomes vary from person to person. Influencers can help raise awareness about skincare, but personal experience should never be taken as medical proof,' he says, adding that trust in this area 'ultimately must come from clinical expertise and responsible patient care.'
Instead of chasing influencer viral cycles, his clinic prioritizes expert-led educational content, media engagement, and public awareness initiatives. He asserts: 'Trust is also built during consultations, when patients receive realistic expectations, understand potential risks, and learn about alternatives. This approach focuses more on clinical validity than online popularity. In aesthetic care, sustainable trust stems from transparent communication, professional competence, and consistent commitment to patient well-being.'
Protection against performance marketing, direct messages, and teleconsultations. The regulatory reform affects not only Instagram reels; it transforms the entire digital sales funnel used by modern cosmetic chains. Historically, aesthetic marketing heavily relied on aggressive performance campaigns. Clickbait advertisements claiming 'Get smooth skin in 3 days' or 'Call now for 50% off hair transplant' were specifically designed to exploit appearance-related insecurities, directly fueling pay-per-lead models.
Under the new guidelines, performance marketing must be purged of high-pressure tactics, artificial urgency, and guaranteed outcome claims. Dr. Vivek Gupta emphasizes that digital visibility must remain factual and compliant with medical ethics. 'Campaigns must avoid guaranteed results, misleading claims, promotional patient testimonials, and messages exploiting appearance-related insecurities,' he states, adding that marketing agencies must understand these boundaries.
This shift has also necessitated a complete overhaul of digital triage and initial online consultations. Previously, potential patients could leave a comment under a video or send a direct message (DM) describing skin issues, receiving direct prescriptions or treatment quotes from social media managers. Dr. Gupta highlights the vital difference between general inquiries and actual consultations, noting: 'Digital messages can provide basic information, but individual treatment recommendations require appropriate clinical assessment.'
Teleconsultations require safeguards such as identity verification, informed consent, confidentiality, and proper documentation. 'Photos sent online may not contain enough information to determine treatment suitability. Where a physical examination or detailed assessment is needed, patients should be advised to attend an in-person consultation,' he warns, concluding that 'convenience must never override clinical judgment, patient confidentiality, or safety.'
When aesthetics goes wrong: The clinical and human cost. When cosmetic procedures are marketed as fast-fashion items, patients pay a high price in their physical and financial well-being. Both dermatologists and plastic surgeons often find themselves in the role of correctors, tasked with...
2